
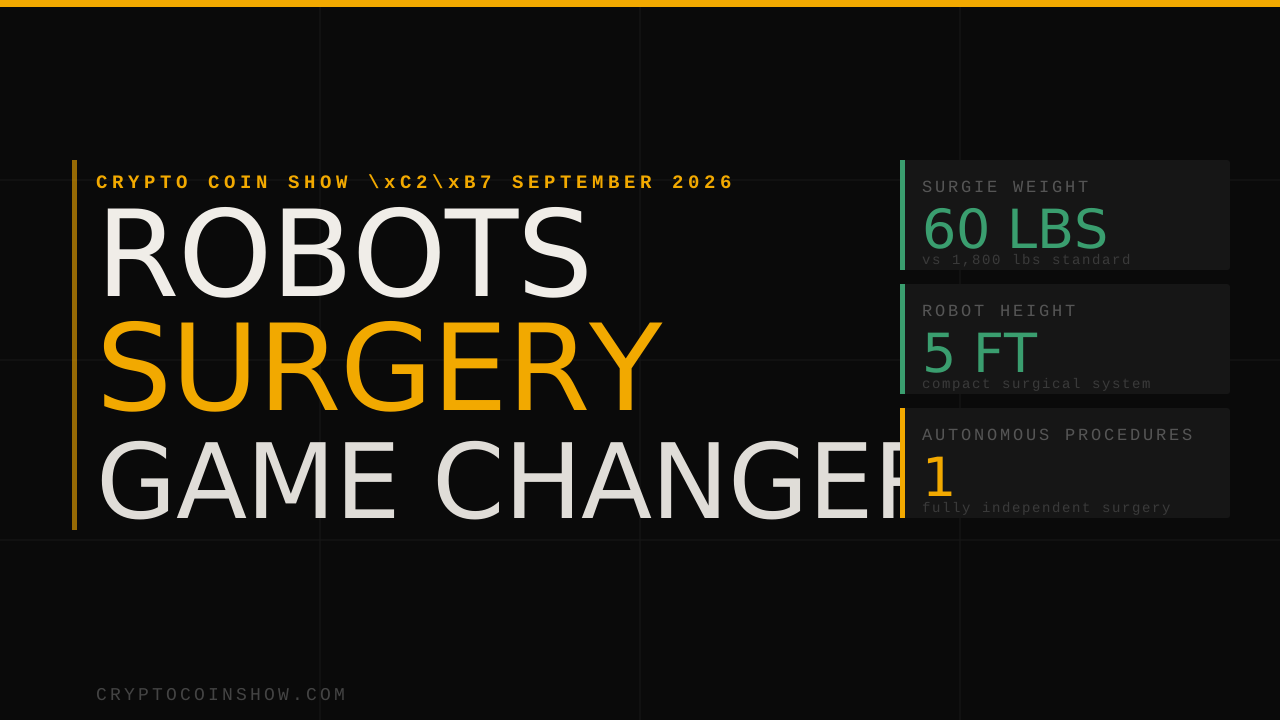
UC San Diego humanoid robots perform live surgery in world first
Humanoid robots have successfully performed live surgery for the first time, marking a potential breakthrough in extending surgical access to underserved regions where specialized operating room equipment cannot reach. For institutional investors evaluating robotics and healthcare technology, this development signals a new category of distributed surgical systems that could operate at a fraction of the cost and spatial footprint of existing da Vinci-class platforms.
- Two humanoid robots named Surgie performed surgeries at UC San Diego, with one procedure fully autonomous and both conducted on large mammals.
- Surgie robots weigh 60 pounds and stand 5 feet tall, compared to 1,800 pounds for standard surgical systems already in hospitals.
- The study, published July 8 in Nature, represents the first general-purpose humanoid robot deployment in live surgery, requiring multiple recalibrations during procedures.
- 60 lbs Surgie weight versus 1,800-pound standard surgical robot footprint
- July 8 Publication date of Nature study on first humanoid surgical deployment
- 2 Surgeries completed with one fully autonomous, one human-assisted procedure
Two humanoid robots successfully performed live surgical procedures at the University of California, San Diego, marking the first documented use of general-purpose humanoid machines in operating room settings. The study, published July 8 in Nature, describes how the robots, named Surgie, completed two distinct surgical workflows on large non-primate mammals.
In the first procedure, a surgeon teleoperated one robot alongside human surgical staff; in the second, two Surgie robots operated autonomously without direct human presence at the surgical table.
The achievement underscores a fundamental shift in how the surgical robotics industry might address persistent access barriers in rural and resource-limited settings where specialized operating room infrastructure remains prohibitively expensive and logistically complex.
The deployment targets a specific market inefficiency that traditional surgical robotics have not addressed. Standard platforms like the da Vinci system weigh approximately 1,800 pounds and demand dedicated operating room space, substantial installation costs, and trained technical teams for setup and recalibration.
Surgie represents a radically different form factor: each unit weighs 60 pounds and stands 5 feet tall, bringing the physical and economic barriers of entry down to a level compatible with rural hospitals, field clinics, and resource-constrained healthcare environments.
Shanglei Liu, assistant professor of surgery at UC San Diego School of Medicine and senior author of the study, described the deployment advantage during teleoperation trials.
It’s a fraction of the cost and it takes a fraction of the space in an operating room. So it’s easy to deploy, anywhere from rural areas, to the battlefield, and even to space.
Shanglei Liu, Assistant Professor of Surgery, UC San Diego School of Medicine
The cost differential and modularity signal a potential new market tier in surgical robotics that institutional medical device investors have not yet seen mature at scale.
While the absolute cost figures remain undisclosed in the trial, the engineering simplification, moving from a specialized surgical arm to a general-purpose humanoid frame, eliminates the need for custom room retrofitting and reduces operator training overhead.
Humanoid Design Replaces Specialized Surgical Arm to Access Broader Deployment Markets
The researchers’ central argument for deploying a general-purpose humanoid platform rather than a specialized robotic arm hinges on accessibility and task flexibility.
Michael Yip, a professor of electrical and computer engineering and co-senior author, emphasizes that the global shortage of trained surgeons has created both extended wait times and geographical care gaps that specialized surgical systems cannot address.
A dedicated surgical robot excels at narrow task execution but cannot move independently through a clinic, retrieve instruments, or adapt to workspace constraints outside the operating theater.
Surgie’s humanoid morphology allows it to function across multiple surgical phases and non-surgical tasks within the clinical environment. The engineering team developed custom adapters to interface Surgie’s grippers with standard surgical instruments, avoiding the need for specialized tool libraries that traditional platforms require.
Nikita Thareja, a general surgery resident and study co-author, noted that the integration exceeded expectations: the robots’ movements and tool-holding sequences aligned naturally with existing surgical workflows rather than forcing procedural adaptation around robot constraints.
The researchers positioned Surgie as a surgical assistant first, not a replacement for human surgeons. In near-term deployment scenarios, the humanoid would retrieve instruments mid-procedure, manage tool sterilization, clean the operating field, and handle post-surgical cleanup, tasks that currently consume scarce OR staff capacity.
By automating these auxiliary functions, the system could theoretically free attending surgeons and nurses to manage multiple procedurally concurrent cases or reduce the overall surgical team size in under-resourced settings.
Multiple Recalibrations and Latency Issues Persist in Early Trial Data
The proof-of-concept results, while historically significant, reveal operational constraints that the commercial system must resolve before widespread deployment becomes viable. During both live procedures, Surgie required multiple recalibrations to maintain surgical precision and hand-eye coordination, extending procedure time beyond benchmarks set by conventional systems.
Liu acknowledged this friction, comparing the current maturity level to early iterations of established surgical platforms. The latency in teleoperation, the delay between surgeon input and robotic execution, remains a documented variable in the system, though the Nature publication does not quantify precise millisecond thresholds achieved during the trials.
For fully autonomous procedures, the system must manage real-time visual feedback, tissue response interpretation, and adaptive tool pressure without human intervention, requirements that demand advances in computer vision and force-feedback sensor integration.
The recalibration overhead suggests that Surgie’s learning curve for surgical teams will differ meaningfully from training protocols for established platforms like da Vinci, where surgeons accumulate thousands of hours of standardized interface interaction. The UC San Diego team must now optimize calibration speed and frequency to compete on time-per-case metrics that hospital economics depend on.
Institutional investors should note that this gap directly impacts the system’s return-on-investment case in rural and military deployment scenarios, where operational efficiency drives adoption decisions.
Path to Clinical Deployment Requires Regulatory Pathway and Cost Validation
The Nature publication establishes proof of concept but does not constitute regulatory clearance for clinical use. The U.S. Food and Drug Administration must evaluate Surgie as a medical device, requiring extensive safety documentation, adverse event monitoring protocols, and systematic performance validation across diverse surgical specialties.
The trial’s use of large non-primate mammals satisfies initial animal model requirements but does not substitute for the human trials and expanded animal cohorts that regulatory bodies typically demand before surgical platform approval.
Institutional investors evaluating the commercial opportunity must distinguish between scientific milestone and market readiness.
The proof of concept validates the fundamental engineering premise, that a humanoid robot can execute surgical tasks with precision sufficient for living tissues, but does not confirm that the system can be manufactured at scale, integrated into diverse hospital IT environments, or trained for variability across surgeon skill levels and surgical specialties.
The UC San Diego team has not disclosed timeline projections for regulatory filing, commercial prototype development, or pilot deployment in target markets like rural clinics or military field hospitals.
The cost model also remains unvalidated at scale. While the Surgie design promises lower capital expenditure and reduced space requirements than da Vinci systems, the absolute acquisition cost per unit, recurring maintenance fees, software licensing models, and operator training costs all influence institutional purchasing decisions in ways the trial did not address.
Next Phase: Clinical Trials and Specialty Integration Will Define Commercial Viability
The research team’s stated next priorities center on expanding the procedural scope beyond the initial gallbladder removal and broadening the evidence base across different surgical disciplines.
To justify capital allocation from hospital systems and healthcare networks, Surgie must demonstrate equivalent or superior outcomes compared to conventional surgical approaches across multiple specialties. Orthopedic, vascular, and general surgical procedures would provide the strongest initial validation targets, each representing large procedure volumes in hospital settings.
The autonomous second surgery raises a separate clinical and regulatory question: whether fully automated surgical execution can achieve safety and outcome parity with human-supervised models, or whether telesurgery with real-time human oversight becomes the durable deployment model. This distinction matters significantly for scaling to remote battlefields or space stations, where communication latency or intermittent connectivity